Microscopic Proof: How Piercing Needles Create Clean Holes Without Scarring
Under high-magnification scanning electron microscopy, the mechanics of skin perforation cease to be a matter of personal preference and become a demonstration of physics. When Japanese modification circles examine the query ニードル と は ピアス, translating directly to the mechanics of what a piercing needle actually is, they confront a profound technological divide between retail piercing instruments and clinical body modification. While public fascination often gravitates toward larger engineering marvels, such as when Manhattan's Empire State Building joined hands with the Space Needle for a historic cultural anniversary, documented in a Business Wire Report, the micro-engineering of medical instruments alters human tissue on a cellular scale. The cellular difference between a retail stud gun and a hollow piercing needle is the difference between blunt crush damage and micro-vascular incision.
Spring-loaded piercing guns force a blunt, manufactured earring stud through epidermal layers using raw mechanical kinetic energy. Conversely, an aseptic piercing procedure relies on a surgical steel hollow needle ground with micro-beveled cutting facets that slice a precise crescent pathway through dermis and subcutaneous tissue. That micro-mechanical difference dictates whether the body forms an organized tunnel of skin cells or an inflamed mass of scar tissue.
📌 Key Takeaways:
- Tissue Dynamics: A tri-beveled medical needle slices an intentional, razor-thin pathway, minimizing cellular necrosis and surrounding vascular collapse.
- Mechanical Trauma: Spring-loaded stud guns rely on blunt displacement, crushing dermal micro-vessels and shattering auricular cartilage.
- Clinical Recovery: Sliced tissue forms a stable fistula inside 6 to 12 weeks, whereas blunt trauma extends healing by months and spikes hypertrophic scarring rates.
Histological Reality of the Beveled Medical Needle
A hollow piercing needle functions as a miniaturized scalpel rather than a punch. Manufactured from AISI 316LVM surgical steel or medical-grade implant titanium, the instrument features a tri-beveled tip. Each face of the tip is ground using diamond-wheel polishers to create microscopic cutting edges measured in micrometers. When this beveled medical needle enters the skin, the primary point pierces the stratum corneum while the secondary lateral bevels slice a clean, curved incision.
Because the interior of the needle bore is completely hollow, it does not core out or remove a plug of flesh. Instead, the geometry displaces an exact crescent flap of tissue. This leaves micro-capillary walls intact along the perimeter of the entry channel. Blood flow remains organized, supplying oxygen and localized neutrophils directly to the wound edge.
Histological cross-sections reveal that tissue pierced with a hollow needle demonstrates immediate cellular viability directly along the wound margins. Cells adjacent to the cut edge do not undergo immediate rupture. Consequently, the inflammatory response remains localized, triggering normal hemostasis and signaling fibroblasts to migrate without widespread necrotic debris.
The Blunt-Force Destruction of Spring-Loaded Stud Guns
Spring-activated piercing guns operate on kinetic displacement. The jewelry installed inside these devices is not sharp; it is cast metal with a tapered, blunt end designed to sit in a clasp. To penetrate the body, the gun releases a high-tension spring that rams the stud through the flesh at velocities exceeding 5 to 8 meters per second.
This blunt entry point does not cut. It shatters cellular walls through compressive hydraulic stress. In soft tissue like the earlobe, this creates extensive interstitial bruising, tearing elastomeric fibers and spreading micro-hematomas deep into the lobular fat pad.
When applied to upper ear anatomy, the kinetic energy produces catastrophic cartilage tissue trauma. Auricular cartilage is an avascular structure that relies entirely on the surrounding perichondrium for nutrient and oxygen diffusion. The blunt force of a stud gun fractures the delicate chondrocyte matrix, separating the cartilage plate from its perichondrial sheath. This separation triggers traumatic perichondritis, permanent deformities, and severe localized necrosis that can require surgical debridement.
Needle Gauge Sizing and Fluid Channel Mechanics
Precision body modification requires matching the needle diameter directly to the chosen jewelry profile to prevent mechanical tension. Piercing needle gauge sizes follow the American Wire Gauge (AWG) or Stubs system, stepping down in external diameter as the gauge number rises:
- 18 Gauge (1.0 mm): Reserved for delicate nostril piercings and small-scale lobe projects.
- 16 Gauge (1.2 mm): The global benchmark for cartilage piercings, including helix, tragus, and conch placements.
- 14 Gauge (1.6 mm): Standard for naval, tongue, and industrial piercings requiring higher structural rigidity.
- 12 Gauge (2.0 mm) and larger: Used for heavy-gauge earlobes and specialized structural modifications.
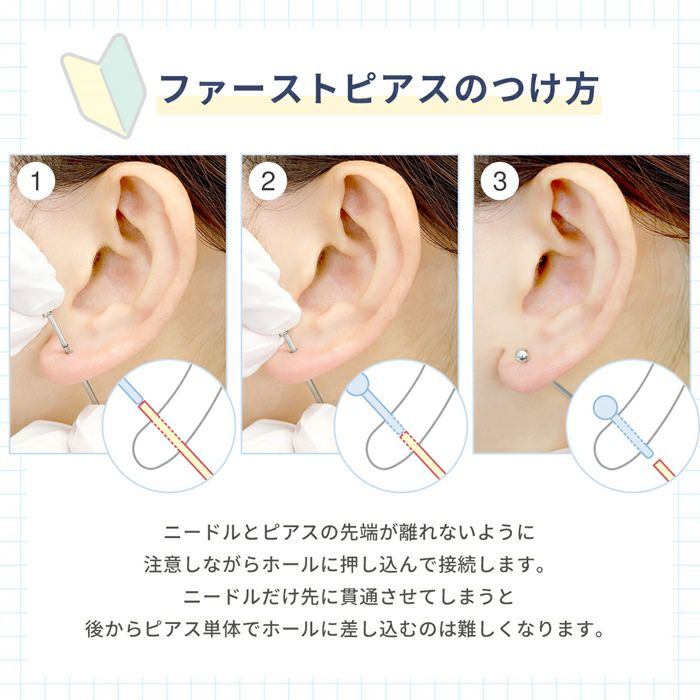
Modern practitioners deploy two primary needle methods: the standard surgical steel hollow needle and the cannula needle piercing system. A cannula needle incorporates a medical-grade Teflon or plastic sleeve over the steel core. Once the needle traverses the tissue, the steel blade withdraws, leaving the flexible plastic tube inside the channel. The piercer slides the sterile jewelry into the sleeve and guides it through with zero friction against the raw wound margin.
Direct needle transfers achieve an identical low-friction outcome through receiving tubes or internally threaded taper pins. In both approaches, the newly created wound experiences almost zero mechanical shear during jewelry insertion.

Fistula Healing Dynamics and Scar Prevention
The ultimate objective of any piercing is the formation of a fistula: an invaginated, fully epithelialized cylinder of skin that connects the entry and exit points. The fistula healing process mirrors the body’s response to a surgical drain or clean incision.
When created cleanly by a hollow needle, basal keratinocytes at the cut epidermal edge begin migrating downward along the tract within 24 to 48 hours. These migrating cells track inward along a clean scaffold of fibrin and fibronectin. Within 14 to 28 days, the epithelial bridge closes from both ends toward the center, forming a continuous layer of protective squamous tissue.
Hollow Needle Pathway:
[Sharp Incision] ──> [Intact Capillaries] ──> [Rapid Keratinocyte Migration] ──> [Smooth Fistula]
Stud Gun Pathway:
[Blunt Impact] ──> [Cellular Necrosis] ──> [Disorganized Granulation] ──> [Hypertrophic Scar/Keloid]
When tissue is crushed by a piercing gun, the wound path is filled with jagged, necrotic cellular debris. Keratinocytes cannot migrate over dead tissue. The wound halts in an extended inflammatory phase. This chronic irritation prompts runaway collagen production, driving hypertrophic tissue formation and elevating the risk of keloid formation in genetically predisposed individuals. For long-term keloid and scar prevention, maintaining the anatomical integrity of the surrounding vascular bed is non-negotiable.
Performance Metrics: Needle Incision Versus Mechanical Impact
Clinical observation and histological data demonstrate stark differences between controlled surgical piercings and uncontrolled kinetic punctures across healing trajectories, tissue response, and complication rates:
| Metric / Parameter | Tri-Bevel Hollow Needle | Mechanical Piercing Gun |
|---|---|---|
| Cutting Geometry | Tri-faceted surgical edge; crescent slice | Blunt stud point; mechanical burst entry |
| Cartilage Trauma Index | Low (0.1, 0.2 mm localized margin) | Severe (multi-radial structural micro-fractures) |
| Ear Piercing Healing Time (Lobe) | 6, 8 weeks | 12, 20 weeks (prolonged by exudate & crushing) |
| Cartilage Healing Time (Helix) | 6, 9 months | 12, 18 months (frequent chronic failure) |
| Sterilization Protocol | Class-B vacuum autoclave / EO gas; 100% single-use | Surface alcohol wipe; non-autoclavable plastic |
| Hypertrophic Scarring Risk | Under 4% with correct aftercare | Exceeds 30% on cartilage installations |
Aseptic Technique and Pathogen Control
Beyond direct tissue disruption, mechanical piercing guns carry structural biosecurity vulnerabilities. Most reusable piercing guns consist of molded plastic housings holding metal spring components. Because plastic components melt under high heat and steam, these devices cannot undergo autoclaving at 121°C to 134°C.
Wiping down plastic devices with isopropyl alcohol or benzalkonium chloride does not achieve true sterilization. Blood micro-droplets aerosolized during blunt-force impacts deposit deep within the trigger housing. This residual biological matter exposes subsequent clients to cross-contamination hazards, including hepatitis B, hepatitis C, and resistant Staphylococcus aureus strains.
Professional studios counter these risks using a rigorous, multi-step sterile body piercing technique:
- Individual Packaging: Every surgical needle arrives sealed in a medical-grade blister pack, sterilized via ethylene oxide (EO) gas or gamma irradiation, marked with chemical integration indicators.
- Medical Barrier Controls: Practitioners utilize sterile surgical gloves, skin prep solutions featuring chlorhexidine gluconate or providone-iodine, and single-use sterile drapes.
- Direct Waste Stream: Needles never contact a secondary surface. Immediately after passing through tissue and transferring jewelry, the instrument drops straight into a rigid biohazard sharps container for destruction.
Frequently Asked Questions (FAQ)
Q1: Does a hollow piercing needle hurt more than a piercing gun?
A1: No. A piercing needle creates far less pain. Because a hollow needle is surgically sharp, it glides through skin with minimal resistance, triggering only a brief, localized sting. Piercing guns rely on blunt force, producing intense blunt-force trauma, deep throbbing, and extended burning sensations that linger for hours.
Q2: Why do piercing guns still exist in retail malls if needles are clinically superior?
A2: Piercing guns persist primarily due to commercial convenience, low labor overhead, and retail tradition. Operating a spring gun requires minimal technical training compared to the years of apprenticeship necessary to master freehand needle angles, depth calibration, and aseptic theater management. However, regulatory health authorities worldwide continue to discourage their use on cartilaginous structures.
Q3: Can a damaged cartilage piercing from a gun be rescued using needle techniques?
A3: If a cartilage piercing done by a gun develops severe angle drift, chronic infection, or hypertrophic bumps, removing the jewelry and allowing the collapsed tissue to heal completely is typically required. Once the tissue stabilizes and deep induration resolves, usually after 3 to 6 months, a professional piercer can assess whether the area can be safely re-pierced using a precision surgical needle.
Clinical Standards for Safe Body Modification
The physical response of human tissue to puncture wounds is governed by direct biological principles: clean cuts heal via organized regeneration, while crushed wounds mend via prolonged inflammation and disorganized scarring. The design of the surgical hollow piercing needle treats body modification as a clinical minor procedure rather than a casual retail purchase.
For anyone pursuing a new ear or body piercing, selecting a trained professional who uses single-use, hollow-beveled needles in an aseptic environment is the most critical decision in preventing long-term tissue trauma. Minimizing cellular injury at the moment of entry sets the foundation for an uncompromised fistula, protects delicate cartilage architecture, and ensures uncomplicated healing.


